Cataratta e chirurgia della cataratta
Revisione paritaria di Dr Philippa Vincent, MRCGPUltimo aggiornamento di Dr Toni Hazell, FRCGPUltimo aggiornamento 29 Lug 2026
Rispetta le linee guida editoriali
- ScaricaScarica
- Condividi
- Language
- Discussione
- Ask Patient
- Versione audio
- Aggiungi alle fonti preferite su Google
Professionisti Medici
Gli articoli di riferimento professionale sono progettati per essere utilizzati dai professionisti della salute. Sono scritti da medici del Regno Unito e basati su prove di ricerca, linee guida del Regno Unito ed europee. Potresti trovare il Cataratta articolo più utile, o uno dei nostri altri articoli sulla salute.
Cataracts are lens opacities. Some are small and do not need treatment but they often become large enough to block light and obstruct vision.
Eziologia1
Ageing is the main cause of cataract development in the developed world, although they can also form congenitally and after various forms of injury to the lens. In the developing world other factors contribute, including malnutrition, acute dehydrating illnesses and excess ultraviolet (UV) exposure. Lack of access to treatment makes them a leading cause of sight loss worldwide.
Epidemiologia2
The prevalence of cataract increases with age: a systematic review found the pooled prevalence (the prevalence of members of samples pooled together) of any cataract was:
20-39 years - 3.01%.
40-59 years - 16.97%
Over 60 years - 54.38%.
A UK study that randomly sampled 1,547 people of 65 years of age and older found that the prevalence of visually-impairing cataracts was:
71% in people aged over 85 years.
59% in people aged 80-84 years.
42% in people aged 75-79 years.
24% in people aged 70-74 years.
16% in people aged 65-69 years.
Cataracts are uncommon in children.
Globally, cataracts are the world's leading cause of sight loss. About 36 million people worldwide have lost their sight, and in over 12 million of them this is due to cataract.
Fattori di rischio1
Apart from age, the most significant types of cataract risk factors in the developed world are:
Fumo.
Diabetes mellitus.
Systemic corticosteroids.
Other risk factors contributing to cataract formation include:
Trauma oculare.
Sesso femminile.
Uveite.
UV exposure.
Poor nutrizione.
Status socio-economico inferiore.
Alcol.
Toxins - eg, drugs of misuse.
Dehydrating illness crises.
Metabolic disorders - eg, galactosaemia in children.
Inflammatory and degenerative eye diseases.
Genetic studies estimate that the heritability of an age-related cataract is around 50%.
Evidence that topical (including inhaled) steroids alone increase the risk of cataract formation is unclear, but there is some evidence to suggest an increased risk from long-term use of steroid eye drops and topical steroids on the peri-orbital skin.3 4
In the developing world the main extrinsic factors are:
Diet (malnutrition).
Acute dehydrating diseases.
Cumulative exposure to sunlight.
In developing countries, cataracts are common in young adults and may be associated with atopy and with diabetes.
Cataracts and diet5
The development of acquired cataract is principally caused by oxidative damage, which naturally leads to consideration of ameliorating this damage by increasing the amount of antioxidants in the diet. However, no strategy has provided convincing evidence of effectiveness in slowing cataract growth, although a 2023 review suggested that the incidence may be less in those who eat more plant-based products.6
Future research needs to take into account the underlying physiology of how specific nutrients and antioxidants are delivered, taken up and metabolised to maintain and restore antioxidant levels in the different regions of the lens.
Fisiopatologia7 8
The lens continues to grow after birth, with the new secondary fibres being added as outer layers. New lens fibres are generated from the lens epithelium. Old fibres are not removed.
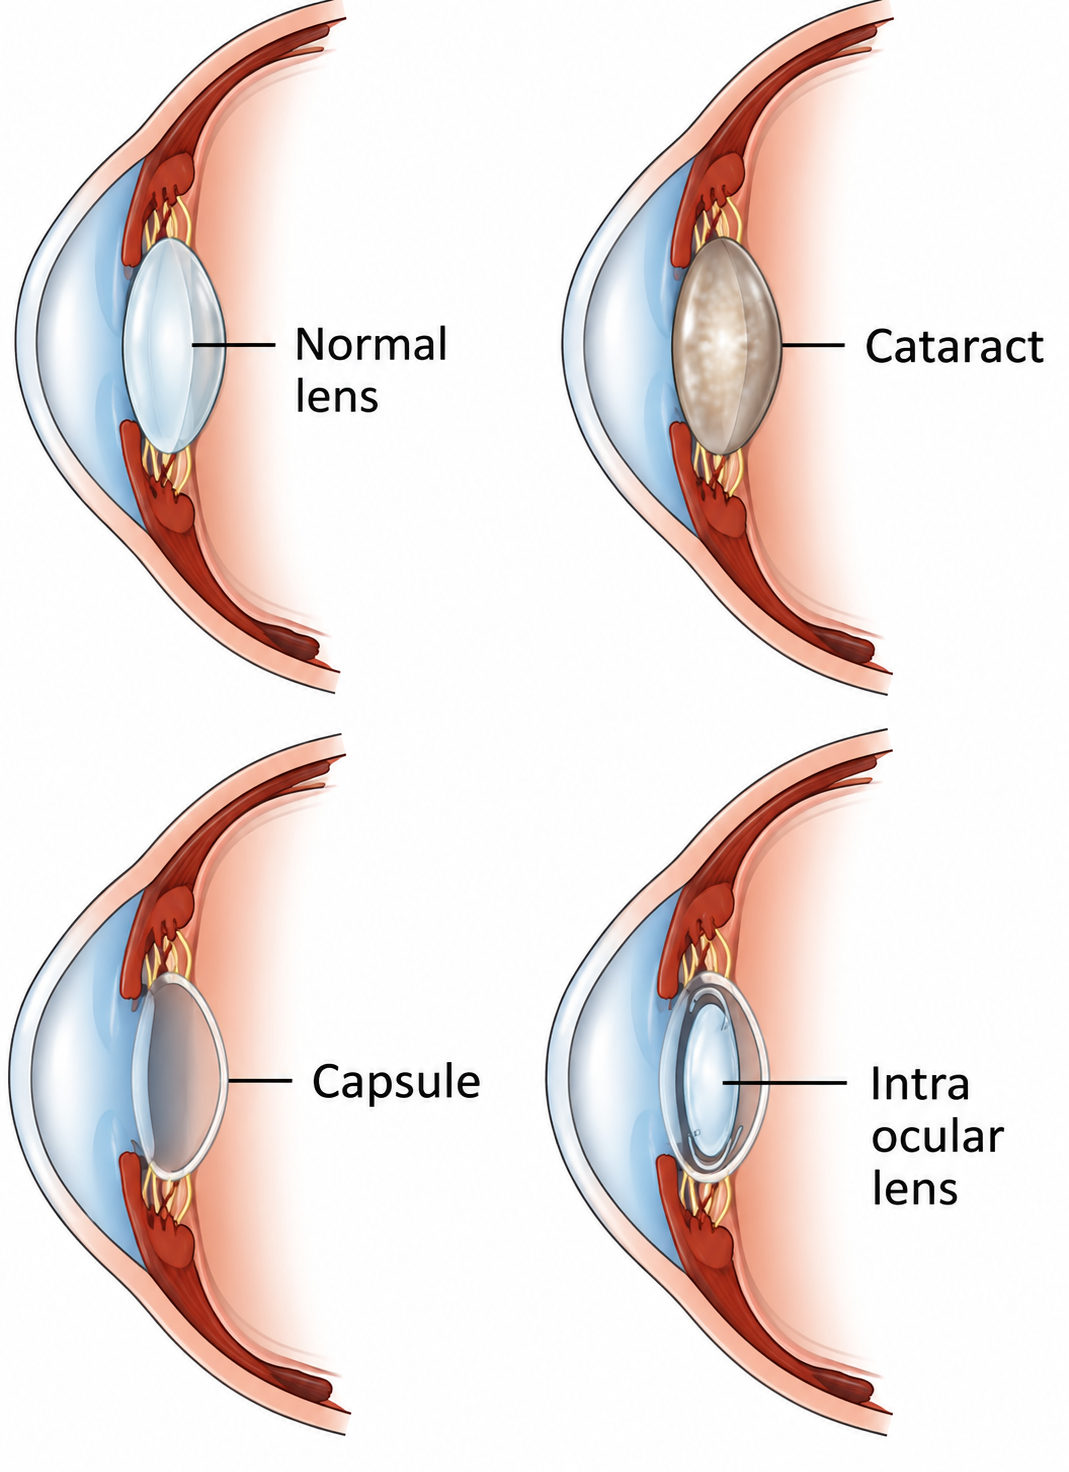
Lens transparency is maintained by many factors, including its microscopic structure and chemistry. The lens has three main parts: the capsule, the epithelium and the fibres. The lens has no nerves, blood vessels, or connective tissue.
The lens capsule is elastic and is composed of collagen.
The lens epithelium, in the anterior portion of the lens between the capsule and the fibres, regulates the homeostasis of the lens and constantly lays down new fibres.
The lens fibres form the bulk of the lens. They are long, thin, transparent cells, arranged lengthwise from the posterior to the anterior poles. They are stacked arranged in concentric layers. They have no nuclei and are composed mainly of crystallins (water-soluble proteins). The transparency of the lens is maintained by the arrangements of these fibres, their lack of intracellular bodies like nuclei, and their cytoskeletons which maintain the architecture.
Transparency is maintained by the structure of the lens proteins and by the way they are stacked, linked and aligned. Disruption of the crystallin fibres will affect the integrity of the carefully composed structure, leading to protein aggregation. Cataracts result from the deposition of aggregated proteins in the lens, causing clouding, light scattering, double vision and obstruction of vision.
A second contributing factor which occurs with ageing is an accumulation of yellow-brown pigment in the lens. This does not affect image sharpness but it affects colour vision and contrast, so may eventually make reading difficult.9
Presentazione10
Sintomi
This depends upon the size and location of the opacity and whether one or both eyes are affected. The most consistent presenting features are:
Gradual painless loss of vision.
Difficulties with reading.
Failure to recognise faces.
Problems watching TV.
Diplopia in one eye.
Haloes.
Many cataracts present before they are symptomatic, because they are noticed by an optician at a routine eye exam.
Cataracts are often described by the part of the lens that is particularly affected. This also affects their typical presentation. There are many possible subdivisions but three broad categories are generally described:
Nuclear sclerosis: this cataract is formed by new layers of fibre (added with ageing) compressing the nucleus of the lens. Typical symptoms include:
Gradually reduced contrast.
Reduced colour intensity.
Reading which may be surprisingly good for acuity level.
Difficulty in seeing golf balls, car number plates, etc.
Difficulty in recognising faces.
Cortical: new fibres are added to the outside of the lens, which age and produce cortical spokes. These may not produce symptoms unless on the visual axis or the entire cortex is affected when it is 'mature':
Light scatter from opacities.
Problems with glare when driving, particularly at night.
Difficulty reading.
Daytime activity relatively unaffected as the iris is constricted.
Posterior subcapsular: opacities in the central posterior cortex. This may occur in younger patients and may cause glare ± deterioration in near vision:
Visually disabling in good lighting - less trouble at low light levels when the pupil is dilated.
Difficulty in daytime driving.
Difficulty in reading.
Paediatric cataracts2
These may be:
Congenital : hereditary/genetic, metabolic (eg, galactosaemia), in-utero infection (toxoplasmosis, other, rubella, cytomegalovirus, herpes simplex (TORCH)).
Developmental: genetic, metabolic (eg, galactokinase deficiency).
Acquired: metabolic (eg, diabetes mellitus), traumatic, post-radiotherapy.
The most common cause of congenital cataracts is infection - rubella (the most common), measles, chickenpox, cytomegalovirus, herpes simplex, herpes zoster, poliomyelitis, influenza, Epstein-Barr virus, syphilis and toxoplasmosis. Other causes are metabolic and genetic syndromes.
Segni
Opacities can be seen as defects in the red reflex obtained when the ophthalmoscope is held 60 cm from the eye. This is best seen with a dilated pupil.
The lens may appear brown or white when a bright light is shone on the eye.
Check that:
Visual acuity is not improved by viewing test through a pinhole.
The patient can indicate where a light is placed.
Pupillary reactions are normal.
Diagnosi differenziale
Gestione1
There is no proven prevention or medical treatment for a cataract. Modern cataract surgery involves lens extraction and replacement. The technique can be intracapsular or extracapsular, although intracapsular extraction is now rarely performed. Surgical removal of the cataract is the only effective treatment to restore or maintain vision.
In the developed world, cataracts are easily treated before vision is severely impaired. In the developing world, cataracts lead to significant problems of severe visual impairment. This is because most people do not seek advice until the cataract is advanced or the eye has developed lens-induced glaucoma, a painful condition. This is partly due to lack of awareness and partly due to a lack of government or socially funded healthcare in countries where socio-economic conditions are poor. Many countries lack sufficient clinicians to meet demand, particularly in rural areas.
Chirurgia della cataratta210
There is no absolute threshold of visual acuity at which surgery is indicated. The National Institute for Health and Care Excellence (NICE) advises that the decision to refer a person with a cataract for surgery should be based on a discussion with them that includes: how the cataract affects the person's vision and quality of life; whether one or both eyes are affected; what cataract surgery involves, including possible risks and benefits; how the person's quality of life may be affected if they choose not to have cataract surgery and whether the person wants to have cataract surgery. It states that access to cataract surgery should not be restricted on the basis of visual acuity.
Cataratta
Complicazioni1
Cataract surgery is a safe and successful procedure in the majority of cases. Poor vision after cataract surgery is generally due to:
Inadequate correction of refractive error postoperatively.
Failure to detect pre-existing eye conditions. Serious co-existing eye conditions such as glaucoma, age-related macular degeneration, diabetic retinopathy e amblyopia are often present in patients requiring cataract surgery.
Surgical complications.
The most common complication is capsular rupture with vitreous loss, which is significant, as it is often associated with a poorer outcome. It also increases the risk of endophthalmitis, which is rare but devastating.
Complicazioni precoci
Posterior capsule rupture with or without loss of vitreous (1-3%).
Protruding or broken sutures.
Trauma to the iris.
Wound gape or prolapse of iris (<1%).
Anterior chamber haemorrhage (<1%).
Vitreous haemorrhage (<1%).
Choroidal haemorrhage (<1%).
Endoftalmite - a devastating but rare condition which occurs in less than 0.5% of cases. Staphylococcus epidermidis is the most common infecting organism.
Refractory uveitis due to low-grade infection. This can be avoided by intraoperative antibiotic prophylaxis.
Complicazioni tardive1
Posterior capsule opacification - this is a late complication (around 40%) and is the most common finding. Vision can usually be restored with laser capsulotomy.
Cystoid edema maculare, more frequently diagnosed by angiography (1%).
Distacco della retina, which can occur weeks, months or even years later. The lifetime risk is about 1 per 150 operations, more likely in case of high myopia.
Open-angle glaucoma (<1%).
Closed-angle glaucoma (<1%).
Bullous keratopathy (a rare complication).
Dysphotopsias:
Negative and positive dysphotopsias are unwanted optical phenomena occurring after cataract surgery due to intraocular light artefacts reflecting off the IOL.
They are the main cause of post-surgical dissatisfaction and are seen in up to two-thirds of patients immediately after cataract surgery, but only around 2-3% after a year. 11
Positive dysphotopsia (glare, haloes and starbursts) is largely attributed to edge effects of the implant, whilst negative dysphotopsia appears related to the patient's anatomical structure.
There are no comprehensive figures on outcomes of cataract surgery in developing countries and on the relative importance of spectacles, patient selection and surgery. However, at least 25% of the six million cataract operations performed annually in developing countries are believed to have poor outcomes. About one quarter of these are due to surgical complications.12
Prognosi12
Adulti
Age-related cataracts are progressive and the progression is variable and unpredictable. Without treatment, most people with a cataract will develop severe visual impairment.
The visual performance of the eye is generally considered in terms of acuity, contrast sensitivity, glare disability, visual fields, and colour vision. Outcomes for cataract surgery have mainly been assessed in terms of acuity only.
The 2024 National Ophthalmology Database Audit found that the risk of severe complications continues to fall - to 0.79% for posterior capsule rupture, 0.48% for vision loss and 0.21% for severe vision loss. 13
With surgery, 95% of people will have 6/12 best corrected vision if there is nothing else wrong with the eye.
More recent studies have looked at self-reporting of outcomes and these make it clear that patients may consider surgery unsuccessful in the face of improved visual acuity if, for example, anisometropia or disturbance from the fellow eye results.
Pre-operative visually significant ocular comorbidity was the most important predictor of poor subjective outcome. Older age was not per se. The greatest benefit was seen for second eye surgery in younger patients.
Patients may be disappointed to find that they require glasses for distant vision after cataract surgery, when they did not require them prior to surgery.
Bambini
Untreated cataracts in children younger than 10 years of age cause amblyopia, leading to lifelong visual impairment even if the cataracts are later removed.
Most children with a unilateral cataract have normal vision in the eye without the cataract. Most children who have treatment for bilateral cataracts achieve only partial sight.
Guida14
Advise the patient not to drive and to contact the DVLA if they cannot meet the criteria listed below. That is likely to be the case where there are severe bilateral cataracts, or after failed bilateral cataract extractions:
Group 1 entitlement (to drive a car or motorcycle)
Per leggere in buona luce diurna (con l'ausilio di occhiali o lenti a contatto se indossati) una targa di immatricolazione fissata a un veicolo a motore e contenente lettere e cifre alte 79 millimetri e larghe 50 millimetri a una distanza di 20 metri, o a una distanza di 20,5 metri dove i caratteri sono alti 79 millimetri e larghi 57 millimetri.
L'acuità visiva (con l'uso di occhiali o lenti a contatto se necessario) deve essere almeno 6/12 con entrambi gli occhi aperti (o nell'unico occhio se si vede con un solo occhio).
Si noti che in presenza di cataratta, l'abbagliamento può influire sulla tua capacità di soddisfare i requisiti della targa, anche se la tua acuità visiva è sufficiente.
Group 2 entitlement (to drive a larger vehicle)
To have a visual acuity, using corrective lenses if necessary, of at least 6/7.5 (0.8 decimal) in the better eye and at least 6/12 (0.5 decimal) in the other eye.
The uncorrected acuity in each eye must be at least 3/60.
Where glasses are worn to meet the minimum standards, they should have a corrective power ≤+8 dioptres.
It is also necessary for all drivers of Group 2 vehicles to be able to meet the prescribed and relevant Group 1 visual acuity requirements.
In the presence of a cataract, glare may affect the ability to meet the number plate requirement, even with appropriate acuities.
If there is any uncertainty about fitness to drive, advise the patient to contact the DVLA or to seek clarification from an eye specialist.
La Dott.ssa Mary Lowth è un'autrice o l'autrice originale di questo opuscolo.
Aggiornamenti esclusivi per i professionisti sanitari
Rimani informato con gli ultimi aggiornamenti clinici, approfondimenti professionali e linee guida basate su evidenze. La newsletter Patient Pro seleziona contenuti essenziali per i professionisti sanitari—consegnati direttamente nella tua casella di posta.
Abbonandoti accetti i nostri Informativa sulla Privacy. Puoi annullare l'iscrizione in qualsiasi momento. Non vendiamo mai i tuoi dati.
Ulteriori letture e riferimenti
- Nizami AA, Gulani AC; Cataract
- Cataratta; NICE CKS, marzo 2025 (accesso solo Regno Unito)
- Daniel BS, Orchard D; Ocular side-effects of topical corticosteroids: what a dermatologist needs to know. Australas J Dermatol. 2015 Aug;56(3):164-9. doi: 10.1111/ajd.12292. Epub 2015 Mar 5.
- Kramer M, Tomkins-Netzer O; Cataract Risk and Topical Corticosteroids among Children with Juvenile Idiopathic Arthritis-Related Uveitis. Ophthalmology. 2020 Apr;127(4S):S19-S20. doi: 10.1016/j.ophtha.2019.10.042.
- Braakhuis AJ, Donaldson CI, Lim JC, et al; Nutritional Strategies to Prevent Lens Cataract: Current Status and Future Strategies. Nutrients. 2019 May 27;11(5). pii: nu11051186. doi: 10.3390/nu11051186.
- Falkowska M, Mlynarczyk M, Micun Z, et al; Influence of Diet, Dietary Products and Vitamins on Age-Related Cataract Incidence: A Systematic Review. Nutrients. 2023 Oct 28;15(21):4585. doi: 10.3390/nu15214585.
- Zhao L, Chen XJ, Zhu J, et al; Il lanosterolo inverte l'aggregazione proteica nelle cataratte. Nature. 30 luglio 2015; 523(7562): 607-11. doi: 10.1038/nature14650. Epub 22 luglio 2015.
- Andley UP; Effects of alpha-crystallin on lens cell function and cataract pathology. Curr Mol Med. 2009 Sep;9(7):887-92.
- Allen D, Vasavada A; Cataract and surgery for cataract. BMJ. 2006 Jul 15;333(7559):128-32. doi: 10.1136/bmj.333.7559.128.
- ; Linee guida NICE (Nov 2017)
- Pusnik A, Petrovski G, Lumi X; Dysphotopsias or Unwanted Visual Phenomena after Cataract Surgery. Life (Basel). 2022 Dec 24;13(1):53. doi: 10.3390/life13010053.
- Yorston D; Cataract complications. Community Eye Health. 2008 Mar;21(65):1-3.
- Latest audit figures show increase in numbers and outcomes of cataract procedures; Royal College of Ophthalmologists, May 2024
- Valutazione dell'idoneità alla guida: guida per i professionisti medici; Agenzia per la Licenza di Guida e Veicoli
Informazioni sull'autoreVisualizza il profilo completo
Aggiornato da

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
La Dott.ssa Toni Hazell si è laureata presso la St. Mary’s Hospital Medical School e ha completato il suo VTS al Northwick Park Hospital.
Informazioni sul recensoreVisualizza il profilo completo

Dr Philippa Vincent, MRCGP
Medico di base, Autore medico
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dr Philippa Vincent è un medico di base del NHS che lavora nel nord di Londra.
Accesso semplice a trattamenti affidabili e servizi sanitari online.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.
 Sinusite acuta
 Tonsillite batterica
 Impetigine
 Punture di insetti
 Fuoco di Sant'AntonioInfezioni delle vie urinarie (IVU)
Più in oftalmologia
- Epifora
- Farmaci per gli occhi - prescrizione e somministrazione
- macchia retinica di Förster-Fuchs
- Arterite a cellule giganti
- Distrofie retiniche ereditarie
- Malattie infiammatorie della retina
- Cheratoplastica
- Malattia vascolare retinica non diabetica
- Nistagmo
- Cellulite orbitale e pre-settale
- Glaucoma primario ad angolo aperto
- Ptosi e ritardo della palpebra
- Sarcoidosi
- Fuoco di Sant'Antonio
- L'occhio e le malattie sistemiche
- Sindrome di Tolosa-Hunt
- Toxoplasmosi
- Test e screening della vista nei bambini piccoli
- Difetti del campo visivo